
Ambulance Patient Offload Time (APOT): How to Track It
How to track ambulance patient offload time (APOT): the timestamps that matter, how to chart wall delays objectively, and when crews should escalate.

Ambulance patient offload time (APOT) is the stretch between your rig arriving at the emergency department and the moment hospital staff formally take over care. California, for one, now requires local EMS agencies to set an offload standard of no more than 30 minutes, 90 percent of the time. Tracking APOT well keeps your 911 coverage honest and shows exactly where the delays are coming from.
Every medic knows the feeling. You back into the bay after a rough call and there are six stretchers lined up along the triage hallway. CAD already shows you at the hospital. But you can't leave until a nurse takes report and accepts the patient.
When there's no clean record of those minutes, it's easy for anyone to assume the crew was dragging its feet. Good timestamps end that argument before it starts.
What is APOT and how is it measured?
APOT isn't a single button press. It's an interval with a defined start and a defined stop, and the NEMSIS data standard gives you the two anchors. In the NEMSIS time fields, the offload interval (what most crews call wall time) runs from eTimes.11 (patient arrived at destination) to eTimes.12 (destination patient transfer of care).
The clock starts when you arrive at the ED. It stops when the receiving staff accept the patient, not when you finish wiping down the stretcher.
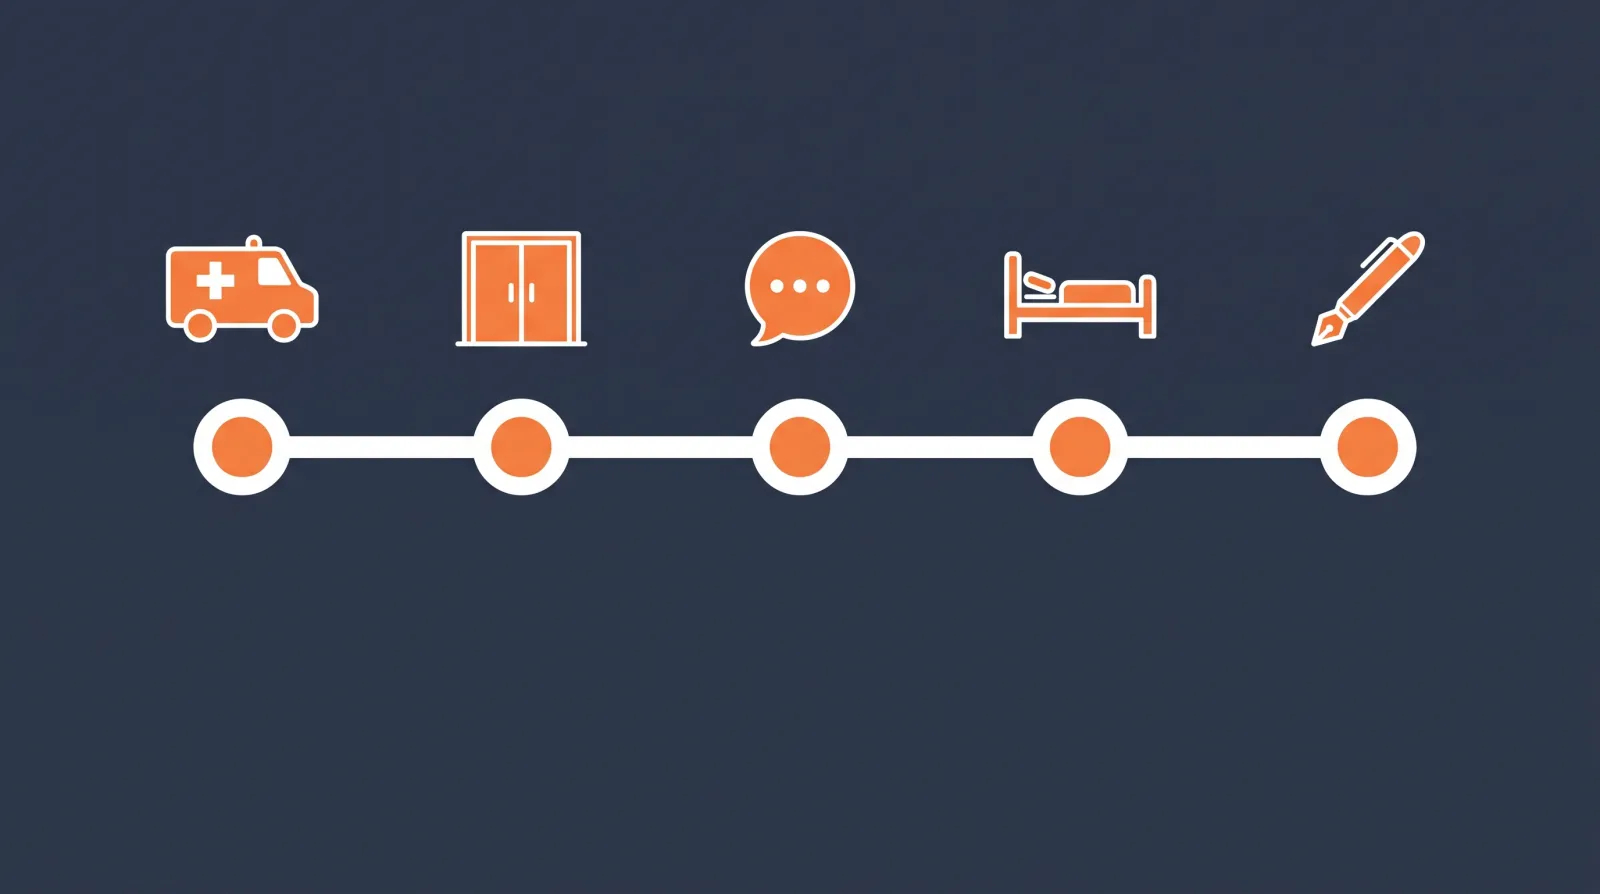
Inside that window, a lot of agencies track a few extra milestones so they can see where the time actually goes:
- Arrival at the emergency department (eTimes.11)
- Entry through the triage doors
- Verbal report started with triage staff
- Patient moved to an ED bed, chair or hallway spot owned by the hospital
- Transfer of care accepted, usually with a receiving nurse signature (eTimes.12)
Once care is transferred, the offload interval is over. Restocking, cleaning and paperwork after that point is turnaround time, which is a separate number. Keeping the two apart matters for EMS hospital offload delay compliance, because it shows whether the bottleneck is at triage or back at the rig. If your CAD and monitor clocks don't agree, fix that first; our guide to CAD timestamp and monitor clock mismatches walks through it.
How do wall delays drain 911 coverage?
A unit parked in a hallway for two hours isn't running calls. Somebody else has to cover its area from farther away, so response times stretch across the district. Pull enough units onto the wall at once and you're calling for mutual aid.
The NAEMSP position statement on ambulance diversion and ED offload delay makes the same point from the physician side: offload delay is a system problem, and EMS and hospital leaders have to work on it together.
There's a crew cost too. People got into this work to take care of sick patients, not to babysit a stretcher for an entire shift. Late calls past shift change pile up overtime, and long wall waits wear people down faster than hard calls do.
How should crews chart offload delays?
Stick to facts. A narrative that reads like a complaint causes friction with the hospital and looks bad if the chart ever ends up in front of a lawyer.
Skip lines like "triage nurse ignored our crew" or "hospital was too slow." They tell the reader you were angry, not what happened. Write what you saw and what you did:
- Bed status: "Arrived at triage 01:45. Triage RN stated no monitored beds available. Patient remained on EMS stretcher with continuous monitoring."
- ED events: "Verbal report delayed due to active resuscitation in trauma bay. Crew continued reassessment."
- Ongoing care: Repeat and document vitals on the interval your protocol sets while you wait. That trail shows the patient was never left without care.
- Notifications: Note the time you told your supervisor or dispatch about the delay.
Charting like that protects your crew during reviews, and it gives your leadership facts they can bring to the hospital without starting a fight.
Which timestamps hold up when APOT is questioned?
Times entered from memory at 3 a.m. are the weak link. A tired medic rounding to the nearest five minutes creates mismatches between CAD, the monitor and the chart, and anyone reviewing the call will notice.
Some agencies use CAD status buttons or GPS-based arrival detection so the arrival time is captured automatically when the rig pulls onto hospital property. That gives you an arrival time that matches the dispatch record without anyone having to remember it.
At the other end, a receiving nurse signature captured on the tablet at the bedside gives you a clear transfer of care time with the staff member's name attached. That's much harder to dispute than a time typed in later.
| Milestone | Typical source | NEMSIS element | What it tells you |
|---|---|---|---|
| ED arrival | CAD status or GPS arrival | eTimes.11 | When the offload clock starts |
| Triage entry | Crew tap on the tablet | Local or custom field | When you got through the doors |
| Verbal report | Crew entry | Local or custom field | When the hospital heard the report |
| Bed transfer | Crew entry | Local or custom field | When the patient left your stretcher |
| Transfer of care | Receiving nurse signature | eTimes.12 | When the offload clock stops |
For more on getting these elements right in your state submissions, see our NEMSIS 3.5.1 field prep guide. If you want to check how well your chart times line up with dispatch after the fact, a CAD reconciliation audit is the next step.
When should crews escalate a wall delay?
Sitting quietly on the wall doesn't help anyone. Crews need a clear ladder that tells them who to call and when. Here's an example of what an agency policy might look like; your local EMS agency may already set its own thresholds:
- First check: Remind triage that you're approaching the local offload standard.
- At the local standard: Notify your field supervisor and have dispatch flag the unit as delayed.
- Past the standard: Supervisor calls the ED charge nurse to talk about bed options.
- Extended delay: Leadership reports the delay through whatever process the local EMS agency uses.
Ambulance diversion documentation belongs in the same habit. If the ED is on diversion, chart the advisory time, who you spoke with and whether your local rules let you override diversion for a critical patient.
With a ladder like this in place, nobody on the road has to guess. They know who to call, when, and what happens next.
How does APOT data lead to hospital agreements?
Complaining about wall time rarely changes anything. Hospital leaders need numbers before they'll add staff or change how they take in ambulance patients.
When your agency has clean offload records across thousands of transports, the conversation shifts. You can show an ED its busiest intake hours, its typical waits and the days that fall apart. That's what prehospital wall time tracking is for.
Some systems have tried EMS hospital liaison programs, where a dedicated provider takes over stable patients in a holding area so crews can get back in service. A preliminary study in Prehospital and Disaster Medicine found offload times dropped after one community hospital started such a program. Results will vary, but it's the kind of fix that only gets funded when someone brings data to the table.
What does good APOT tracking look like on a real call?
Frequently asked questions
Is it abandonment to leave a patient on the wall?
Generally, yes. Abandonment means ending care without handing the patient off to a provider at an equal or higher level. Until the receiving staff accept the patient, they're still yours. Check your state rules and local protocols for the exact standard.
Can crews take a meal break while waiting on the wall?
Not while the patient is still in your care. Until transfer of care happens, you're responsible for that patient. Your agency's policy should spell out how breaks are handled during long offload delays.
Do states penalize hospitals for long APOT delays?
It depends on where you work. California's AB 40 requires local EMS agencies to set an offload standard of no more than 30 minutes, 90 percent of the time, and requires hospitals to file an APOT reduction protocol with the state EMS authority. Other states handle it differently, so check with your state or local EMS agency.
How does diversion status affect incoming ambulances?
Diversion tells dispatch an ED is asking ambulances to go elsewhere when possible. Many regional policies still let crews take unstable patients to the closest appropriate hospital regardless of diversion. Chart the diversion status and any override on the run report.
Why does a receiving nurse signature matter for APOT?
It ties the transfer of care time to a named person at a specific moment. Without it, the transfer time is just a number someone typed, and it's easier for anyone to dispute how long the crew waited. A signature captured on the tablet at the bedside gives you a much stronger record.
Want a closer look at how Mobile Medic captures receiving nurse signatures on glass right on the iPad? See the features.
Sources
- NASEMSO EMS Time Duration Definitions (via NEMSIS) (external site)
- Contra Costa News: Governor Signs AB 40 to Combat Ambulance Patient Offload Delays (external site)
- California AB 40 (2023), chaptered bill text (external site)
- NAEMSP Position Statement: Ambulance Diversion and Emergency Department Offload Delay (external site)
- Prehospital and Disaster Medicine: Impacts of an EMS Hospital Liaison Program on Ambulance Offload Times (external site)


